Ketamine works differently from conventional antidepressant medications. Rather than primarily acting through serotonin or norepinephrine systems, ketamine’s antidepressant effects involve the brain’s glutamate signaling system, including NMDA and AMPA receptors and downstream pathways associated with synaptic plasticity.
For some people with depression, particularly treatment-resistant depression (TRD), this different biological pathway may contribute to antidepressant effects that emerge more rapidly than those typically associated with conventional antidepressant medications. Response varies, and ketamine is not appropriate for everyone.
NY Ketamine Infusions provides medically supervised treatment for appropriately selected patients in New York City and Melville, Long Island.
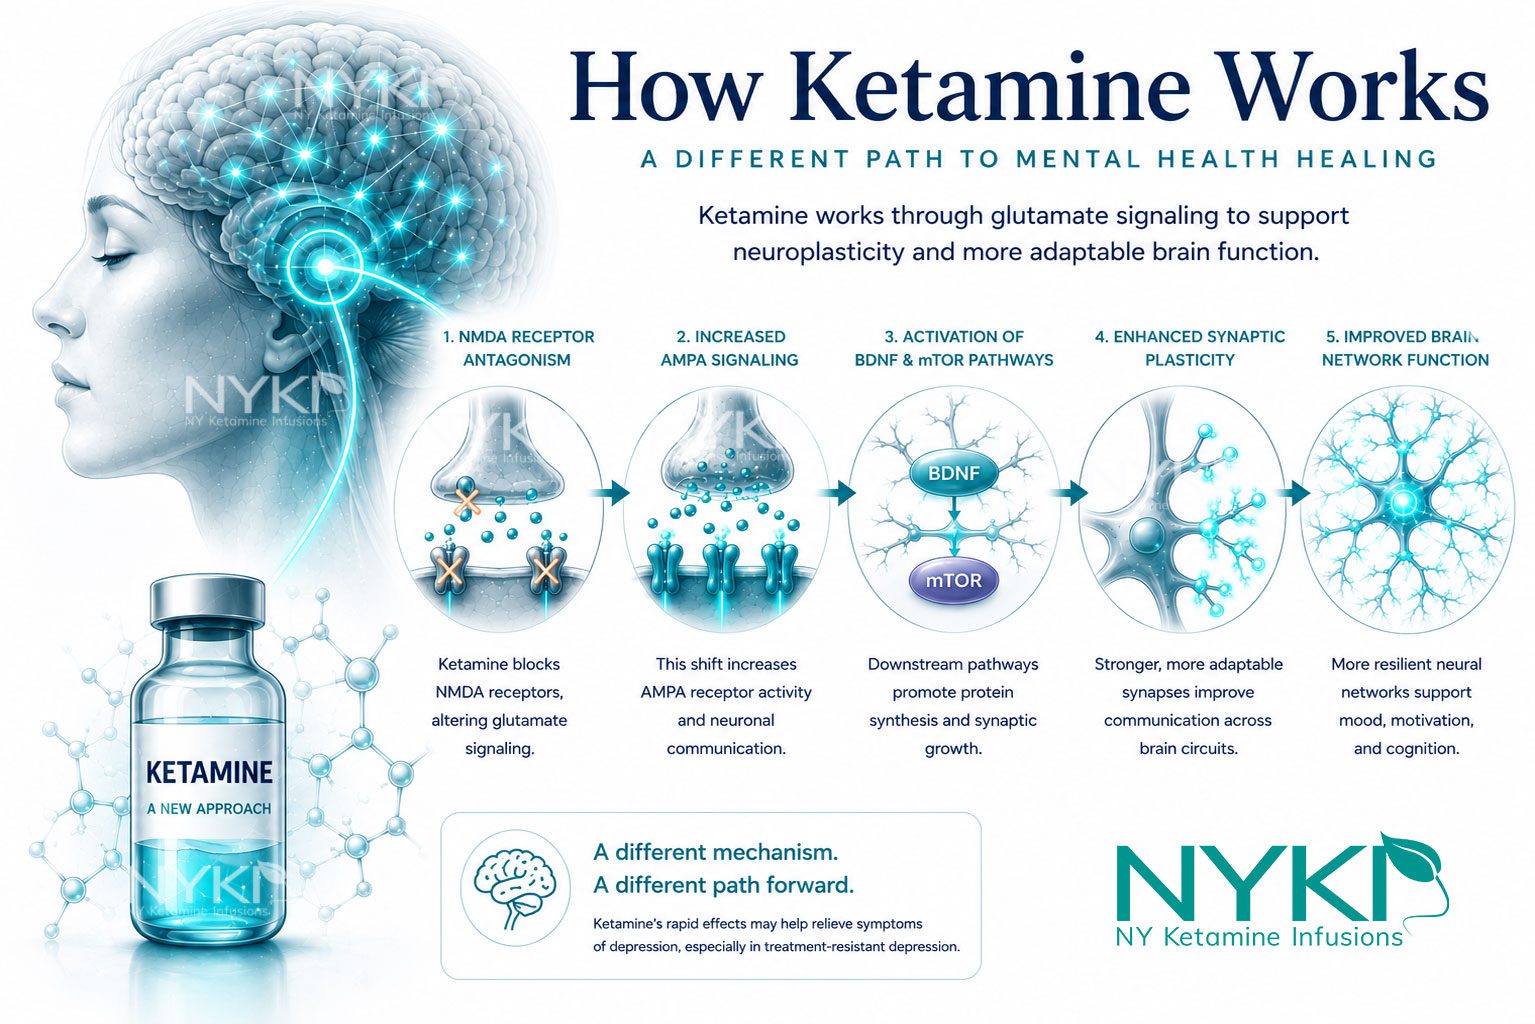
Ketamine blocks NMDA receptors and alters glutamate signaling. This can increase AMPA receptor-mediated activity and engage downstream pathways involving BDNF, TrkB, mTOR, protein synthesis and synaptic plasticity. Researchers believe these processes may help neural connections and brain networks become more adaptable. Ketamine’s complete antidepressant mechanism is still being studied.

Many conventional antidepressants primarily influence monoamine neurotransmitter systems such as serotonin and norepinephrine. Ketamine takes a different pharmacological route: it is an N-methyl-D-aspartate (NMDA) receptor antagonist, and its antidepressant effects are strongly associated with glutamatergic signaling.
Glutamate is the brain’s major excitatory neurotransmitter and is essential to communication between neurons, learning, memory and synaptic plasticity. By changing NMDA receptor activity, ketamine can alter glutamate signaling and influence AMPA receptors and downstream cellular pathways associated with neural adaptation.
This different mechanism is one reason ketamine has become an important area of research for depression and treatment-resistant depression.
Ketamine infusion treatments are the gold standard for addressing drug-resistant depression, anxiety, PTSD and numerous other mental illnesses
Depression is not simply the result of a single neurotransmitter being “too low.” Major depressive disorder involves complex changes across brain systems involved in mood, motivation, cognition, reward, stress response and emotional regulation.
Chronic stress and depression have also been associated with changes in synaptic function and neuroplasticity. A synapse is the communication point where one neuron signals another. Changes in synaptic efficiency can affect how neural circuits communicate and adapt.
This does not mean depression literally damages or permanently “breaks” the brain. A more accurate model is that depression can be associated with altered communication and adaptability across certain neural circuits.
Ketamine’s antidepressant pharmacology is closely associated with glutamate. Instead of simply raising or lowering one neurotransmitter throughout the brain, ketamine appears to change how glutamate signaling is processed at specific receptors and within relevant neural circuits.
This glutamate-centered mechanism distinguishes ketamine from traditional monoamine-focused antidepressant models and helps explain why researchers study it as a rapid-acting treatment approach.
One of ketamine’s best-established pharmacological actions is antagonism of NMDA receptors, a class of receptors activated by glutamate.
Leading models propose that NMDA receptor blockade can alter the balance of inhibitory and excitatory signaling, including effects involving GABAergic interneurons, and thereby change glutamate transmission. The antidepressant mechanism is more complex than simply “turning off” NMDA receptors; downstream consequences of altered glutamate signaling appear to be important.
A key downstream feature in major mechanistic models is increased signaling through AMPA receptors, another class of glutamate receptor. AMPA receptor activation can increase postsynaptic neuronal activity and initiate intracellular signaling involved in synaptic function.
A useful simplified sequence is:
Ketamine → NMDA receptor modulation → altered glutamate signaling → increased AMPA receptor-mediated signaling
Increased AMPA receptor-mediated signaling can engage interconnected pathways
involved in neuroplasticity. Research has implicated brain-derived neurotrophic factor (BDNF), its receptor TrkB, mechanistic target of rapamycin complex 1 (mTORC1), and pathways involved in protein synthesis and synaptic function.
These mechanisms should not be viewed as isolated switches. They form interacting biological systems that influence how neurons respond to activity and maintain or modify synaptic connections.
BDNF is a protein involved in neuronal function and synaptic plasticity. Ketamine-associated glutamate and AMPA signaling has been linked in experimental research with BDNF-related signaling.
BDNF can activate TrkB receptors, which influence intracellular pathways involved in neural adaptation. This provides one proposed bridge between ketamine’s initial effects on glutamate receptors and downstream changes associated with synaptic plasticity.
BDNF/TrkB-related signaling can interact with pathways involving mTORC1, a regulator of cellular processes including protein synthesis. Ketamine research has linked mTOR-related signaling with production and regulation of proteins important to synaptic structure and function.
This does not mean ketamine instantly “rewires the brain.” A more accurate interpretation is that ketamine-associated signaling may help create biological conditions that support more responsive and adaptable neural connections.
Neuroplasticity is the brain’s capacity to adapt in response to activity, learning, experience and environmental demands. Synaptic plasticity refers more specifically to changes in the strength and effectiveness of communication between neurons.
Preclinical and translational research has associated ketamine with changes involving neuroplasticity-related molecules, synaptic proteins, dendritic spines and synaptic function. These findings are better understood as evidence of adaptive biological processes than as proof of instant brain rewiring.
Changes at individual synapses may influence communication across larger neural circuits. Depression has been associated with altered activity and connectivity in networks involved in emotional regulation, executive function, reward and self-referential processing.
Research continues to investigate how ketamine affects these larger-scale networks. Conceptually, more adaptable communication at the synaptic level may contribute to changes in how broader mood- and cognition-related circuits coordinate.
Many conventional antidepressants require repeated dosing over weeks before meaningful clinical improvement becomes apparent. Ketamine has demonstrated antidepressant effects that can emerge within hours in some research participants, including people with treatment-resistant depression.
Researchers believe the rapid initiation of glutamatergic and neuroplasticity-related signaling may help explain this difference. However, individual response varies: some patients improve rapidly, some improve gradually across a treatment series, and some do not experience a clinically meaningful response.
Treatment-resistant depression generally describes major depression that has not improved adequately after appropriate antidepressant treatment trials. Because ketamine acts through biological pathways that differ from many conventional antidepressants, it may offer an alternative treatment approach for appropriately selected patients with TRD.
Current evidence supports a multifaceted model involving molecular, synaptic, cellular and network-level effects. No single receptor or pathway fully explains every antidepressant effect of ketamine.
Ketamine
↓
NMDA receptor antagonism
↓
Altered glutamate signaling
↓
Enhanced AMPA receptor-mediated signaling
↓
BDNF / TrkB and related intracellular pathways
↓
mTOR-associated protein synthesis
↓
Synaptic plasticity and adaptation
↓
Potential changes in larger mood-related brain networks
↓
Antidepressant effects in some patients
This sequence is intentionally simplified. Ketamine interacts with multiple biological systems, and researchers continue to investigate which mechanisms are necessary for its rapid and sustained antidepressant effects.
Ketamine’s pharmacology extends beyond NMDA and AMPA receptors. Research has examined interactions involving GABAergic, monoaminergic, opioid, inflammatory, cholinergic and other signaling systems, as well as ketamine metabolites. These proposed mechanisms are not necessarily mutually exclusive.
For patient education, the glutamate–NMDA–AMPA–plasticity model remains a useful way to understand the best-studied sequence while recognizing that the complete mechanism is still evolving.
The phrase “rewires the brain” is commonly used but can oversimplify the science. Experimental research has identified changes involving dendritic spines, synaptic proteins, synaptic function and neuroplasticity after ketamine exposure.
A more accurate explanation is that ketamine-associated signaling may support biological processes that help existing neural connections become more adaptable and responsive. Structural remodeling can occur in experimental models, but these effects should not be presented as instantaneous or guaranteed in an individual patient.
(important section for transparency and authority)
IV racemic ketamine is FDA-approved as an anesthetic, but IV ketamine is not FDA-approved specifically for depression. Its use for depression and treatment-resistant depression is therefore an off-label medical use.
Esketamine nasal spray(Spravato) is a related but distinct treatment with specific FDA-approved psychiatric indications. Patients comparing IV ketamine and esketamine should discuss the differences, eligibility requirements, benefits and risks with a qualified clinician.
NY Ketamine Infusions provides medically supervised treatment for eligible patients in New York City and Melville, Long Island. Patients considering ketamine for depression or treatment-resistant depression receive an evaluation to determine whether treatment may be appropriate based on diagnosis, medical history, prior treatment response, current medications and other clinical factors.
For people searching for ketamine treatment in New York, ketamine therapy in NYC, or treatment-resistant depression care on Long Island, the goal of an evaluation is not simply to determine whether ketamine is available—it is to determine whether it is clinically appropriate for the individual patient.
Ketamine blocks NMDA receptors and alters glutamate signaling. This can increase AMPA receptor-mediated activity and influence downstream pathways associated with BDNF, TrkB, mTOR, protein synthesis, synaptic plasticity and neural-network function. Scientists continue to investigate how these mechanisms combine to produce antidepressant effects.
Many conventional antidepressants primarily act through monoamine systems such as serotonin and norepinephrine. Ketamine’s antidepressant effects prominently involve glutamate signaling, NMDA receptor antagonism, AMPA receptor activity and downstream neuroplasticity-related pathways.
An antagonist reduces or blocks activation of a receptor. Ketamine functions as an NMDA receptor antagonist, changing how glutamate-mediated signaling occurs through NMDA receptors and contributing to downstream signaling effects.
AMPA receptors are glutamate receptors involved in excitatory communication between neurons. Increased AMPA receptor-mediated signaling is considered an important downstream component of several leading models of ketamine’s antidepressant mechanism.
BDNF is a protein involved in neuronal function and synaptic plasticity, while mTOR is part of a cellular signaling system that regulates processes including protein synthesis. Both have been implicated in research on ketamine’s downstream neuroplasticity-related effects.
“Rewiring” is an oversimplification. Ketamine-associated signaling may support synaptic plasticity and biological processes that help neural connections become more adaptable and responsive. The timing and clinical significance of structural changes vary and remain an active area of research.
One leading explanation is that ketamine rapidly alters glutamate signaling and engages downstream pathways related to synaptic plasticity. Antidepressant effects have emerged within hours in some studies, but not every patient responds and the timing of improvement varies.
Clinical research supports antidepressant effects of ketamine in some people with treatment-resistant depression. Because it acts through pathways that differ from many conventional antidepressants, it may be considered for appropriately selected patients who have not improved adequately with previous treatments.
No. IV racemic ketamine is FDA-approved as an anesthetic, but its use for depression is off-label. Esketamine nasal spray is a related but distinct treatment with specific FDA-approved psychiatric indications.
NY Ketamine Infusions provides medically supervised treatment for eligible patients in New York City and Melville, Long Island. A clinical evaluation is required to determine whether ketamine is appropriate for an individual patient.
NY Ketamine Infusions provides advanced Ketamine therapy and SPRAVATO® treatment options for patients throughout New York City and Long Island. With locations serving Lower Manhattan and Melville, our team welcomes patients from nearby Manhattan, Brooklyn, western Suffolk County, eastern Nassau County, and surrounding communities. We help patients explore mental health services and treatment options for anxiety, depression, PTSD, OCD, Bipolar Disorder, Alcohol Dependence, and Treatment-resistant Depression (TRD) in a supportive clinical setting.